Treatment can do more than target a tumour: it can reopen blocked bile flow, reduce jaundice and itching, treat cholangitis, and create a path to longer survival when the disease is removable or controllable. By the end, you will know how tumour location, stage, diagnosis, and treatment setting shape the benefits you can realistically expect and what to ask a specialist in Pune.
Key takeaways
- Tumour location and stage determine whether surgery can remove all visible cancer.
- MRI, CT, MRCP, biopsy and blood tests help confirm cholangiocarcinoma.
- Bile drainage can relieve jaundice when a tumour blocks the bile duct.
- Ask whether surgery, systemic treatment, radiation or transplant evaluation fits your case.
How tumour location and stage determine the benefits you can receive
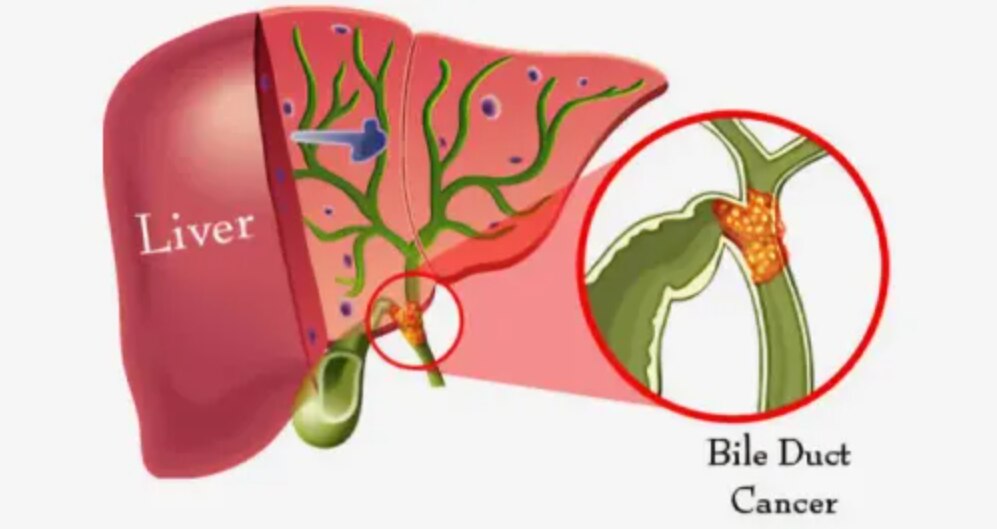
Tumour location determines which structures must be removed or protected, while stage determines whether treatment can remove all visible disease. That is why a bile duct cancer specialist in Pune should identify the subtype, vessel involvement, lymph nodes, and distant spread before recommending an operation.
| Location | Typical treatment focus | Potential benefit |
|---|---|---|
| Intrahepatic | Liver resection, sometimes with bile-duct reconstruction | Removes a localised tumour and can provide long-term control when clear margins are achievable |
| Perihilar (hilar or Klatskin) | Bile-duct excision with partial liver resection; selected patients may enter a transplant protocol | Restores drainage and can offer curative treatment in carefully selected cases |
| Distal | Pancreaticoduodenectomy (Whipple procedure) for suitable tumours | Removes the tumour and affected duct, pancreas, and duodenum when complete resection is possible |
Early, localised cancer offers the strongest chance of complete removal. The benefit depends on clear microscopic margins and adequate lymph-node assessment; involvement of major vessels, extensive lymph nodes, or metastases can make surgery unsafe or non-curative.
Ask the treatment team to explain these points:
- Whether the cancer is resectable, borderline resectable, locally advanced, or metastatic
- Whether jaundice, itching, infection, or obstruction needs drainage before treatment
- Whether selected perihilar transplantation criteria apply; spread, nodal disease, metastases, poor fitness, or protocol rules can exclude it
- Whether chemotherapy, radiation, immunotherapy, or targeted treatment can control unresectable disease and extend survival
- Which tissue tests are relevant, including FGFR2, IDH1, BRAF V600E, HER2, MSI-high, mismatch-repair deficiency, or NTRK
Even when cure is impossible, treatment can relieve symptoms, control growth, treat cholangitis, and support comfort. These are important benefits of bile duct cancer treatment in Pune.
Which tests confirm bile duct cancer and rule out other causes
Obstructive jaundice needs prompt assessment, especially with dark urine, pale stools, itching, weight loss, fever, or worsening abdominal pain. Doctors check bilirubin, alkaline phosphatase, alanine aminotransferase, aspartate aminotransferase, blood counts, and infection markers, then use ultrasound followed by multiphase contrast CT or MRI with MRCP.
Imaging shows where the narrowing lies, whether a mass involves the liver, gallbladder, pancreas, vessels, or lymph nodes, and whether cancer has spread. The pattern still needs tissue confirmation in most cases. ERCP allows bile drainage plus brush cytology or forceps biopsy; endoscopic ultrasound can sample a mass or lymph node.
A bile duct cancer specialist in Pune should review the actual scans and pathology, not rely only on a written report.
| Cause | Findings that point toward it | How doctors separate it |
|---|---|---|
| Stones | Mobile stones or duct widening on ultrasound or MRCP; colicky pain | ERCP may remove the stone; cytology does not show cancer |
| Cholangitis | Fever, chills, right-upper-abdominal pain, raised white-cell count | Infection improves after antibiotics and drainage; a persistent mass needs sampling |
| Pancreatic cancer | Mass in the pancreatic head on CT or EUS | EUS biopsy identifies pancreatic tissue |
| Gallbladder cancer | Gallbladder wall mass or liver invasion | Imaging and biopsy locate the primary tumour |
| Benign stricture | Smooth, short narrowing after surgery, pancreatitis, or injury | Follow-up imaging and repeated sampling show no malignant cells |
- Complete staging includes CT of the chest, abdomen, and pelvis; PET-CT is selective.
- Seek emergency care for jaundice with fever, confusion, low blood pressure, or severe pain.
What surgery, drainage, and transplant can achieve
Treatment can remove cholangiocarcinoma when scans show that surgeons can take out the tumour with clear microscopic margins and assess nearby lymph nodes. Intrahepatic disease may require liver resection; perihilar disease may require bile-duct excision, liver resection, and reconstruction; selected distal tumours may need a Whipple procedure.
| Option | What it can achieve | When it applies |
|---|---|---|
| Curative-intent surgery | Remove the tumour and offer the best chance of long-term control or cure | Cancer remains technically resectable, without unresectable spread |
| Selected transplantation | Replace the liver after tumour-directed treatment, with curative intent | Strict protocols for some unresectable perihilar cancers; no disqualifying metastases or nodal disease, and adequate medical fitness |
| Biliary drainage | Lower bilirubin, relieve jaundice and itching, treat or prevent obstruction-related cholangitis, and improve liver function | ERCP stent placement or percutaneous transhepatic drainage when bile cannot flow; before surgery or systemic treatment, or for comfort |
Transplant is not a standard option for most bile duct cancers. Eligible perihilar patients usually need neoadjuvant chemoradiation and review under a specialised protocol; tumour spread, positive nodes, metastases, or poor fitness can exclude transplantation.
Drainage restores flow but does not remove cancer. Stents can block or migrate and cause pancreatitis, bleeding, or bacterial cholangitis; percutaneous drains require tube care. For cholangiocarcinoma treatment in Pune, ask which ducts will be drained, whether drainage supports a planned operation, and which symptoms—especially fever or worsening abdominal pain—need urgent review.
How treatment helps when surgery is not possible
Treatment can still slow locally advanced or metastatic disease, ease obstruction, and extend life when an operation cannot remove all cancer. It is usually a control plan, not a guaranteed cure.
- Chemotherapy, commonly gemcitabine with cisplatin, can shrink or slow tumours and reduce cancer-related symptoms. An immune-checkpoint inhibitor such as durvalumab or pembrolizumab may add disease control for medically suitable patients.
- Targeted therapy uses tumour testing to find changes such as FGFR2 fusion, IDH1 mutation, HER2 amplification, BRAF mutation, or MSI-H/dMMR status. A matching drug can offer control after, or instead of, standard chemotherapy.
- Radiation can control a troublesome tumour near vital structures and relieve pain, bleeding, or obstruction. The radiation team must protect nearby bowel and healthy liver, so tumour position and previous treatment determine feasibility.
- Clinical trials can provide access to newer drugs, combinations, or treatment sequences while contributing to evidence for future patients. Ask about eligibility before starting the next line of treatment.
- Supportive care treats jaundice, itching, infection, nausea, pain, weight loss, and fatigue. Endoscopic stenting or percutaneous drainage can restore bile flow and improve liver function, but drainage alone does not remove cancer.
For bile duct cancer care pcmc, ask who reviews scans and pathology, manages blocked or infected bile ducts urgently, checks molecular results, and coordinates oncology, hepatobiliary surgery, radiation, nutrition, and palliative-care services. That coordination prevents treatment delays and keeps comfort goals alongside tumour control.
How to choose coordinated bile duct cancer care in Pune
Choose a team that coordinates imaging, pathology, drainage, infection control, nutrition, and cancer treatment rather than offering one standard plan. A bile duct cancer doctor near me should explain whether the tumour is intrahepatic, perihilar, or distal, its stage, vascular involvement, lymph nodes, distant spread, and expected future liver remnant.
Before choosing, ask:
- Who reviews the actual CT or MRI/MRCP images, pathology slides, and liver-function results?
- Will a multidisciplinary meeting assess resectability and transplant eligibility before major surgery?
- Which bile-duct segments will be drained, which stent or drain is planned, and who manages blockage, migration, bleeding, pancreatitis, or cholangitis?
- Where should you go at night for fever, worsening abdominal pain, confusion, or increasing jaundice?
- If disease is advanced, will tissue or validated blood testing check FGFR2, IDH1, BRAF V600E, HER2, MSI or mismatch-repair deficiency, and NTRK alterations?
| Team member | Decision it can improve | Safety or treatment benefit |
|---|---|---|
| Hepatobiliary or transplant surgeon | Resectability and future liver remnant | Avoids an unsafe operation and identifies curative or transplant pathways |
| Radiologist and specialist pathologist | Imaging and diagnosis review | Reduces staging or sampling errors |
| Oncologist, radiation oncologist, and hepatologist | Systemic, radiation, and liver-support plans | Matches treatment to tumour biology and liver function |
| Endoscopist and interventional radiologist | Stent or percutaneous drainage | Restores bile flow while limiting procedure-related complications |
Dr Amol Jadhav's Comprehensive Liver Care Center should be assessed by whether it can connect these reviews and emergency services, not by clinic distance alone. A second surgical opinion is sensible before irreversible surgery or an “unresectable” decision.
Frequently asked questions
How do tumour location and stage affect bile duct cancer treatment benefits?
Location shows which bile ducts, liver tissue, blood vessels and nearby organs are involved. Stage shows whether the cancer has spread to lymph nodes or distant organs and whether treatment can remove all visible disease.
Which tests confirm bile duct cancer and rule out other causes?
Doctors use liver function tests, tumour markers, ultrasound, contrast CT, MRI with MRCP, and tissue sampling when needed. These tests help distinguish cholangiocarcinoma from gallstones, infections, strictures and other causes of bile duct blockage.
What can surgery, bile drainage and liver transplantation achieve?
Surgery aims to remove the tumour with clear margins while preserving enough functioning liver. Drainage can reduce jaundice and infection risk when bile flow is blocked. Transplant evaluation applies to selected cancers that meet strict medical criteria.
How can treatment help when bile duct cancer cannot be removed surgically?
Chemotherapy, targeted therapy, immunotherapy, radiation and biliary stents can control disease, relieve symptoms and maintain bile flow. The treatment plan depends on tumour biology, organ function and previous treatment.
How do you choose coordinated bile duct cancer care in Pune?
Choose a team that can review imaging and pathology together, assess surgical and transplant options, manage biliary drainage, and coordinate medical oncology, radiation oncology and supportive care.
Keywords